Early COVID-19 images of swabbing from Wuhan, China, looked more like an Ebola news story — health-care workers fully encased in personal protective equipment (PPE), inserting swabs so deeply that brain injury seemed imminent.
As COVID-19 (and testing) spread around the world, there were reports of “brain scraping”, “brain stabbing” or “brain tickling” swabs. Perhaps this was your experience early in the pandemic. Perhaps these stories have put you off getting tested so far.
But if you go to a drive-through clinic today, you’re likely to have a different swab, one that’s briefly inserted and not so far up as before.
So if fear of the swab itself is holding you back from getting tested, here’s what you need to know about these gentler swabs.
‘Brain scrapers’ not used so much in drive-through clinics
The swabs that gave COVID-19 testing its reputation are the nasopharyngeal swabs. Although these are considered the “gold standard” of testing, they are undeniably uncomfortable.
You remove your mask and blow your nose to clear your nasal passages. Then you try not to sneeze, cough or gag while a health worker inserts a long, flexible shaft about 12cm up your nose and into the back of your throat (until there’s resistance). They then swivel the swab against the back of your throat.
The distance for insertion is significant. Close your eyes and imagine a thin shaft being inserted the length of the space between your nostrils and the outer opening of the ear. The health worker needs to rotate the swab to maximise contact with the contents in the back of the nose before removing it.
The swab may cause your eyes to water, a reflex cough or sneeze. Because of this risk, staff must wear full PPE to avoid risk of being exposed to and inhaling infectious particles and aerosols.
This type of swab is still used in some clinics, and different jurisdictions around the world have different testing policies.
You’ll be pleased to hear, things changed
As the pandemic evolved, so have methods of testing, with evidence accumulating about how well they work.
For instance, some Australians have had their saliva tested, including Victorians towards the start of the state’s second wave.
But more widely used now in a typical drive-through clinic are a combined swab of the throat and nose.
You’ll be pleased to know the health worker swabs your throat first before using the same swab up your nose (and not the other way around)! This is the so-called oropharyngeal/nasal swab.
First the health worker will use a tongue depressor to keep your tongue down, then swab the area behind and next to the tonsils. Then they will take a nose swab.
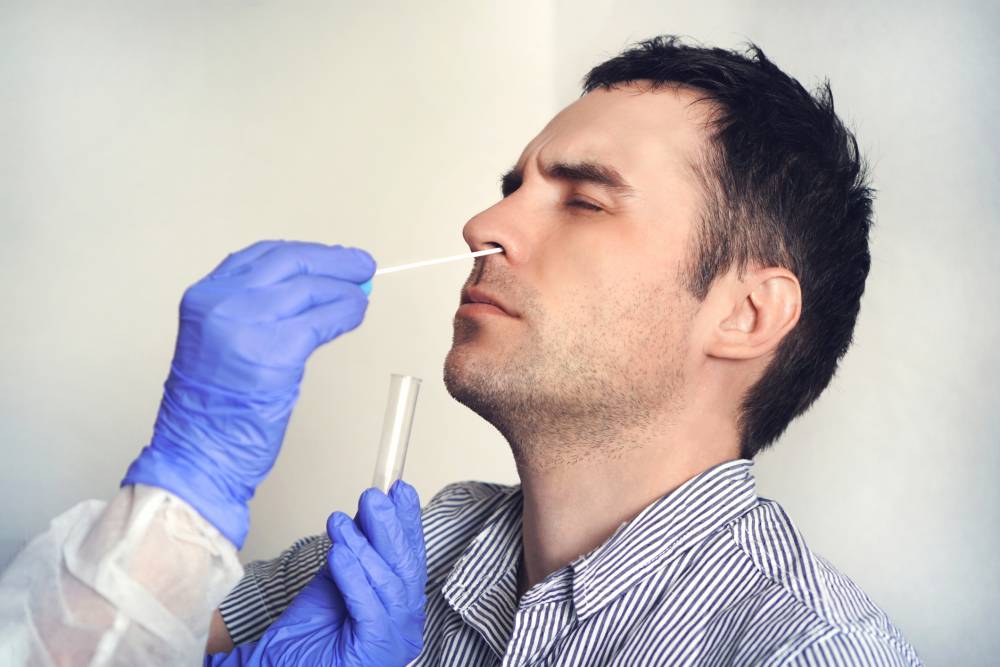
If they take a superficial nose swab, they will ask you to look straight ahead before gently inserting the swab upwards until there’s some resistance. Then they will hold the swab in place for 10-15 seconds while rotating it, before repeating this in the other nostril.
If they take a mid-turbinate nasal (also known as a deep nasal) swab, you will tilt your head back slightly. The health worker will then insert the swab horizontally (instead of vertically) until there’s resistance (about two to three centimetres). They will then gently rotate the swab for 10-15 seconds before repeating on the other side.
Why did the swabs change?
If someone is going to stick a swab stick up our collective noses, the test needs to be accurate and reliable.
But what if other options were almost as good, without so much invasion, coughing and increased exposure risk for health-care workers?
So from late March and into April, organisations including the US Food and Drug Administration and US Centers for Disease Control, and Australia’s Public Health Laboratory Network, announced they would move away from the deeper nasopharyngeal swabs to using nasal swabs for this type of testing.
The recommendation in Australia is to use a combined throat/deep nasal swab but if the health worker thinks it necessary, a nasopharyngeal swab.
Since then, studies suggest the gap between absolute best (nasopharyngeal) and avoiding a gag or cough-inducing reflex (nasal) might not matter as much as once thought.
Comparative studies show throat/nasal swabs are as sensitive as nasopharyngeal to detect SARS-CoV-2, the virus that causes COVID-19.
Other studies show throat/nasal swabs are practical, cheap, accurate and reliable.
Still not convinced? Your brain really is safe
The accumulating evidence suggests the newer nasal swabs are safe, reliable, cheaper to complete, and less unpleasant. They also save expensive, higher grade PPE for where it is needed — in our health-care facilities.
So with testing rates down in Victoria and calls for more testing in New South Wales, this is a reminder we must continue to test, test, test, as well as practise hand hygiene, social distancing, and wearing masks.
This story was originally published on The Conversation by Associate Professor Implementation Science, JBI, University of Adelaide and Clinical Lecturer, University of Adelaide


